
 9 pages

Post-Hospitalization Assessments
After discharge. Understand the needs at home.
Following hospital discharge, a registered nurse (RN) assessment compares the patient’s current condition and support needs with available discharge information.
All services
Following hospital discharge, a registered nurse (RN) assessment compares the patient’s current condition and support needs with available discharge information.
Discharge instructions may introduce changes to medications, activity restrictions and day-to-day support. Share the discharge summary, current medication information, relevant orders and concerns through the document-sharing process agreed with your agency. Identify missing records or unclear instructions for review with the designated clinical contact.
Our coordinator arranges the appointment based on patient availability and RN coverage. The RN verifies and signs the assessment. Our office reviews the documentation and coordinates any required corrections before delivery. Clinical concerns and unresolved instructions are communicated through the process agreed with your agency.
Visit Focus and Agency Handoff
The agreed scope guides preparation, the RN’s visit record and follow-up with your agency.
Review discharge instructions
Provide discharge paperwork, medication information, known restrictions and relevant orders. Identify missing records and the questions that require clarification with your agency’s clinical contact.
Assess current needs at home
The RN reviews the patient’s current condition, ability to manage daily activities and available support against the discharge information, within the agreed assessment scope. Differences affecting care at home are documented for follow-up.
Hand off findings that need action
The visit record identifies medication discrepancies, unresolved instructions and other concerns requiring follow-up. Your agency and the appropriate practitioner address those findings and any required changes to orders or the Plan of Care.
The completed visit record is delivered as a PDF or by authorized entry into your agency’s electronic health record (EHR), as agreed. Where a Plan of Care is prepared or revised, your agency’s Director of Patient Services (DPS) approves it before finalization.
Post-Hospitalization Assessments Documentation
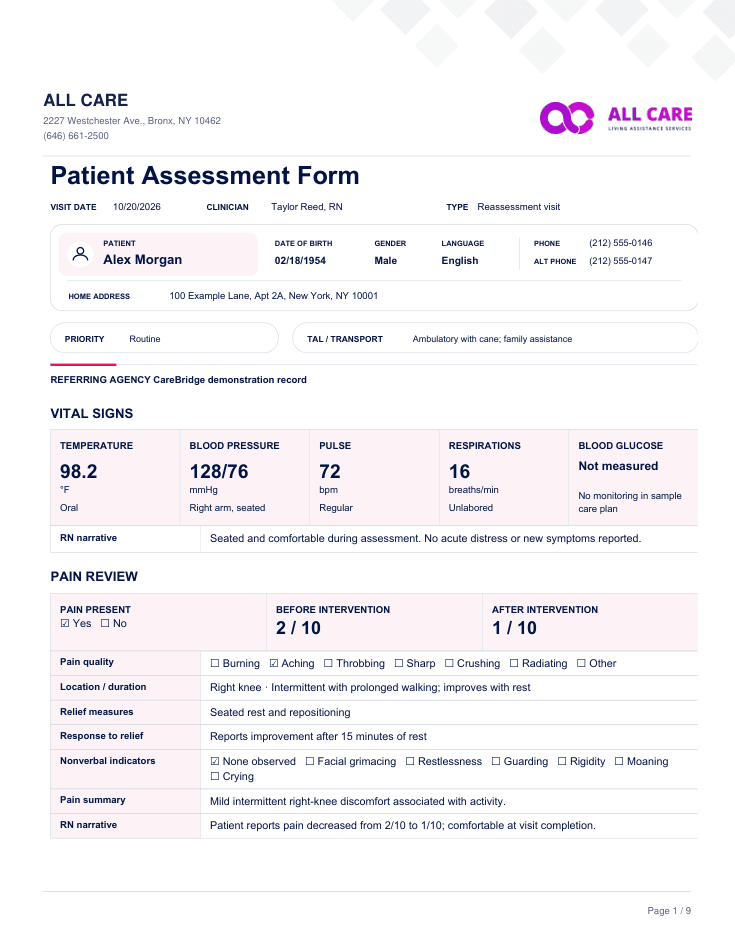
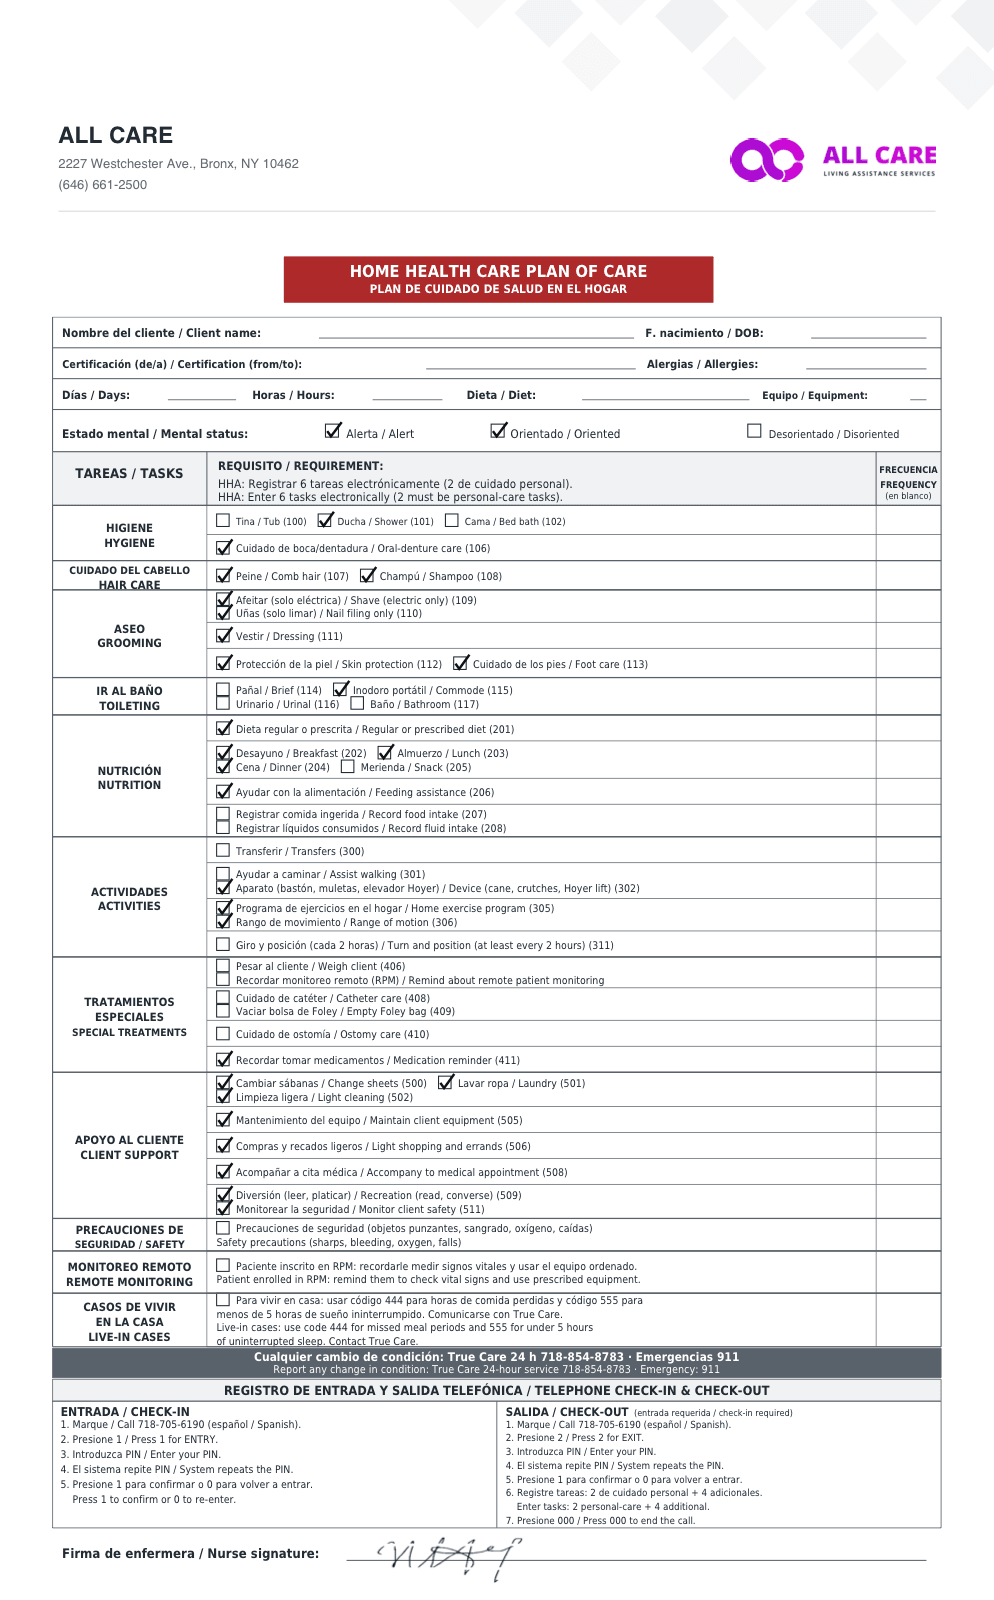
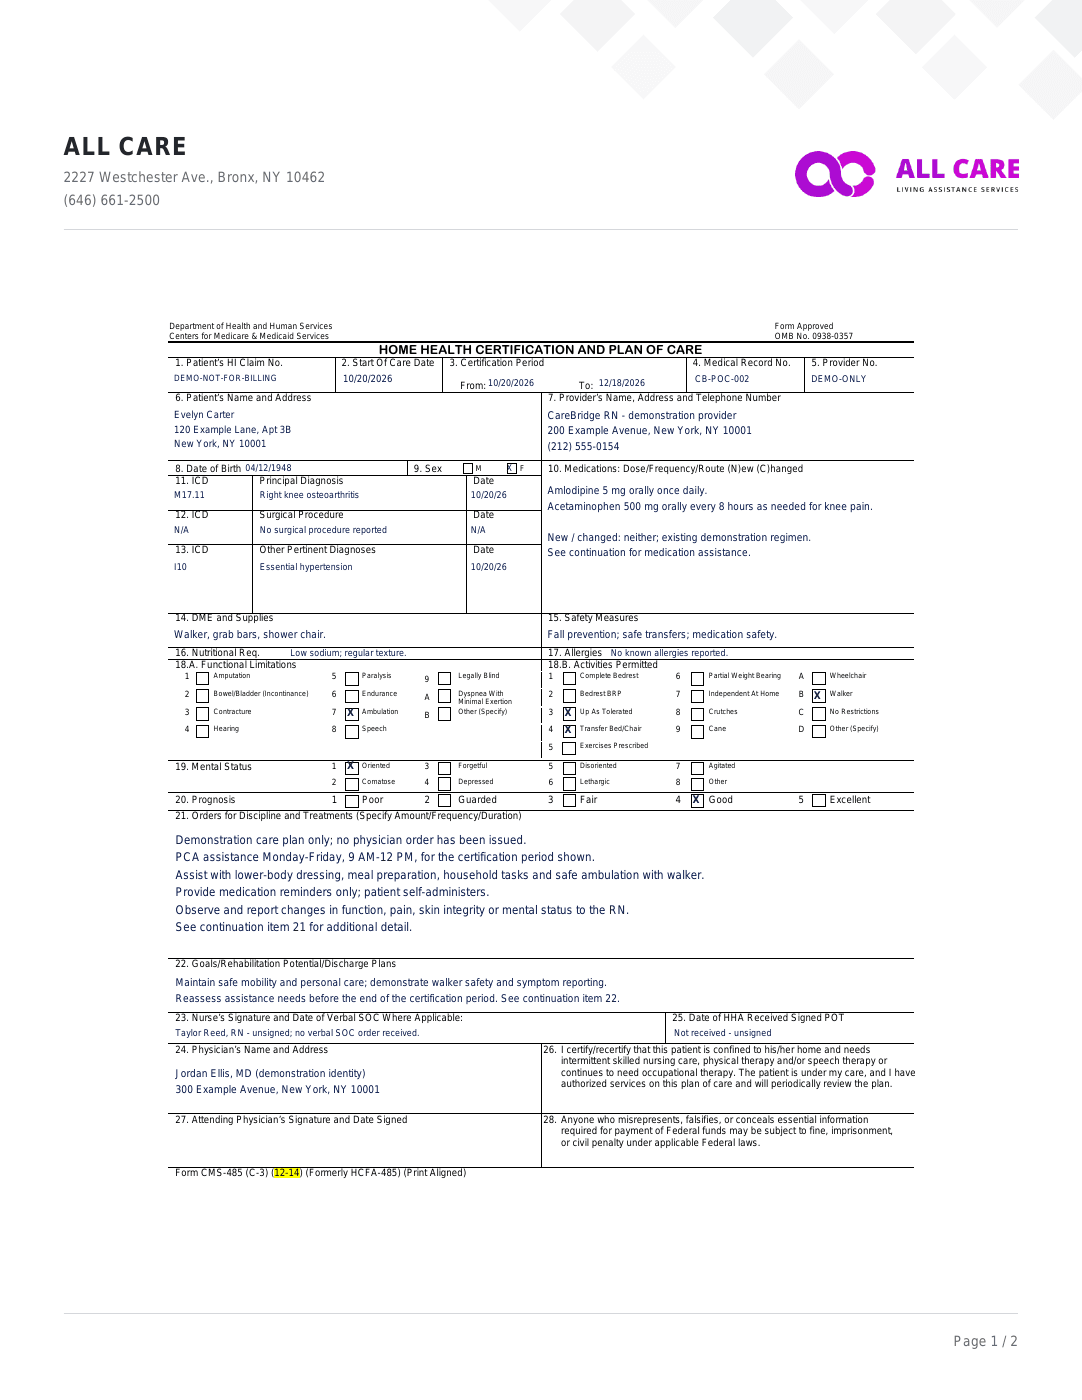
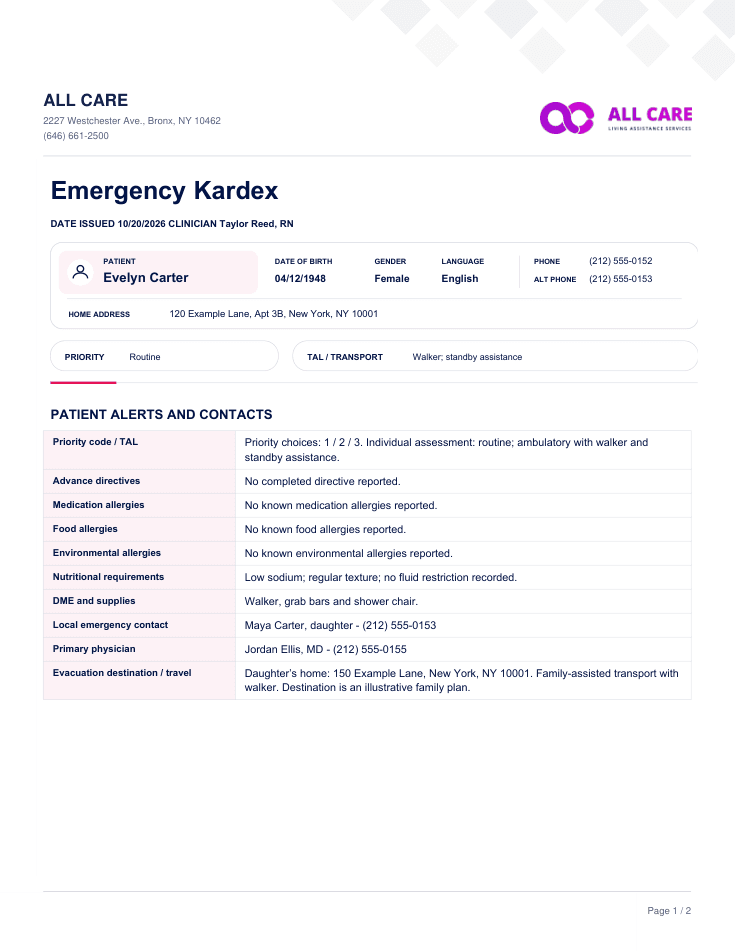
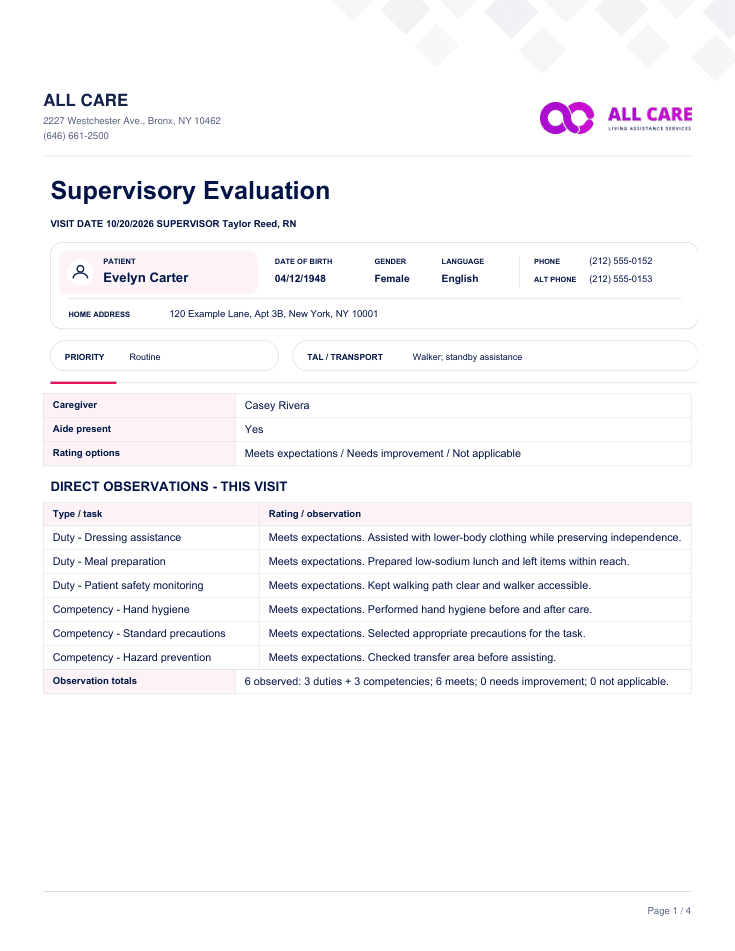
These samples illustrate documents that may support a follow-up visit. The delivered record depends on the assessment type, applicable requirements and the scope agreed with your agency.
Illustrative samples with fictional details. Required forms vary by assignment; these are not issued patient records, treatment orders or legal agreements.
Let’s Coordinate the Next Visit.
Tell us the discharge date, location and requested assessment timing. We will review the scheduling options with you.